


Times are heady in science and technology. The intelligence supply curve looks exponential1, and every field is rightly asking what becomes possible with AI, and what becomes obsolete.
I see a lot of optimism for accelerated progress in longevity (and medicine in general), but the optimism is mostly indefinite. “Better and faster drugs" is very much plausible, but delivering years of healthy life is a process of many steps. As one example, skeptics argue that regardless of abundant intelligence, clinical trials will continue to be slow and expensive. Solving this with ‘better drugs that will yield clear answers faster’ requires us to believe that biomedical R&D will be improved in dramatic ways, exceeding, say, every Nobel-winning discovery of the past century. A big ask, but after witnessing LLMs becoming lawyers by reading reddit and solving novel math problems, perhaps we should let indefinite optimism prevail?
I don’t think so, because the conditions that allowed language models to stampede across knowledge work do not exist for ‘curing disease’. You can’t do reinforcement learning without verifiable outcomes. And the corpus of biological data we’ve collected so far mostly doesn’t contain the right information to provide feedback on “what would be a good treatment for Alzheimer’s”. For AI to accelerate cures we need to start deliberately generating data that contains the answers, and we should start now because the intelligence curve is already outpacing longevity data generation.
The potential impact of AI is huge, and whether we end up curing disease and extending life is too important for hope to be our strategy. The rest of this piece will lay out these assumptions and arguments, and describe the types of data we need to generate to take a revolution in longevity off its indefinite hold.
AI works when it has task-shaped data and verifiable outcomes.
In general, AI has gotten good at tasks when three ingredients exist:
First, sufficient compute.
Second, a massive corpus of training data that establishes base capability.
Richer data is better, but isn’t sufficient unless it contains task-relevant answers.
Third, a feedback system where verifiable outcomes of the relevant task allow the model to improve beyond that base.
The speed and cost of verification for that task determines how fast capability accrues.
Once compute scaled, the first language models cleared all three: Humanity’s historical writings served as training data, and early test environments had clear reward functions like rule-based games, interactive chats where humans respond to output, and code or math with formal verifiers. In each case the act of using the output reveals whether it serves its purpose, such that feedback signals are built into the product.
Biology is physical, and therefore requires physical verification of hypotheses. The data either already exists in a form that (at least latently) contains the information needed for a task, or it has to be generated via physical experiments. AI ingesting all of PubMed doesn’t substitute, because the literature is a highly incomplete and biased projection of biology that provides no feedback signal on new hypotheses. In the case of AlphaFold the data already existed. Three decades of PDB structures combined with sequence databases contained enough structure-sequence pairs for the mapping to be learnable, and CASP’s held-out structures provided ground truth verification data.
But for “how do we treat this disease”, the data we have collected usually clears neither bar. A disease is itself often a label we apply to a pattern of dysfunction we don’t fully understand, with names like heart failure, Alzheimer’s, and sarcopenia grouping together patients whose physiology has gone wrong in similar-looking ways. The label does not by itself tell us about the underlying causal trajectory. The answers about how to reverse physiological decline are not latent in cross-sectional snapshots of postmortem organs with and without disease, and the verification loop is a clinical trial that runs for years. To understand what data we need to generate, we have to ask where in biology the events that produce these labels live.

Task-shaped data in longevity
Curing age-related disease puts specific demands on each of the three criteria above. The data has to contain answers about how organisms change over the course of decades, it has to support causal inference, and the verification loop has to be fast enough that we can iterate on hypotheses.
Biology spans multiple physical layers of organization, each with different behaviors, measurement tools, and iteration speeds. Knowing which layer your question lives at, and which layer your experiments actually probe, is the most important orientation for applying AI to disease.
Layer 1 is molecular. Drug molecules binding to proteins is how we make most medicines, and this is AlphaFold etc territory. For DNA, RNA, and proteins we’re good at simulating biophysics, and experiments can happen as fast as robotic arms can move samples around. Other challenges at this layer, e.g. chemical synthesis and pharmacology, ADME, and off-target effects, are making progress.
Layer 2 is cellular. What’s the response when a protein gets blocked? Some activity stops, the cell changes gene expression to compensate, and ends up in a new steady state (or maybe dies) minutes or hours later. Tools like CRISPR and single-cell sequencing apply here.
Layer 3 is physiological. What happens to an organ when its cells change? Other cells get involved, and the new steady state might be destructive or ineffective. This unfolds as gradual changes and responses over weeks to years. Many of the diseases we hope to cure live at this layer: heart failure, dementia, aging. Age-related multimorbidity is definitionally physiological, since it concerns whole-body systems failing to maintain coordinated function over time.
Layer 4 is organismal. Is the organism alive and functioning, with organs working in concert? If we’re discussing lifespan, and many other clinical trial outcomes, we’re asking questions here.
Higher layers emerge from lower ones, but the mapping is many-to-many. The same molecular state in a cell can produce different physiological outcomes depending on the surrounding tissue, organ-level signaling, and timing, so a lower-layer measurement on its own doesn't determine what's happening above. The true higher layer readout does not exist - a cell cannot have blood pressure. This produces a critical asymmetry that governs how we apply AI to biology: lower layers cannot provide verifiable outcomes for tasks at higher layers. Lower-layer measurements contain higher-layer answers only when the higher-layer outcome was directly measured and linked back to them. The bridge between layers has to be measured into existence, rather than inferred from one side.
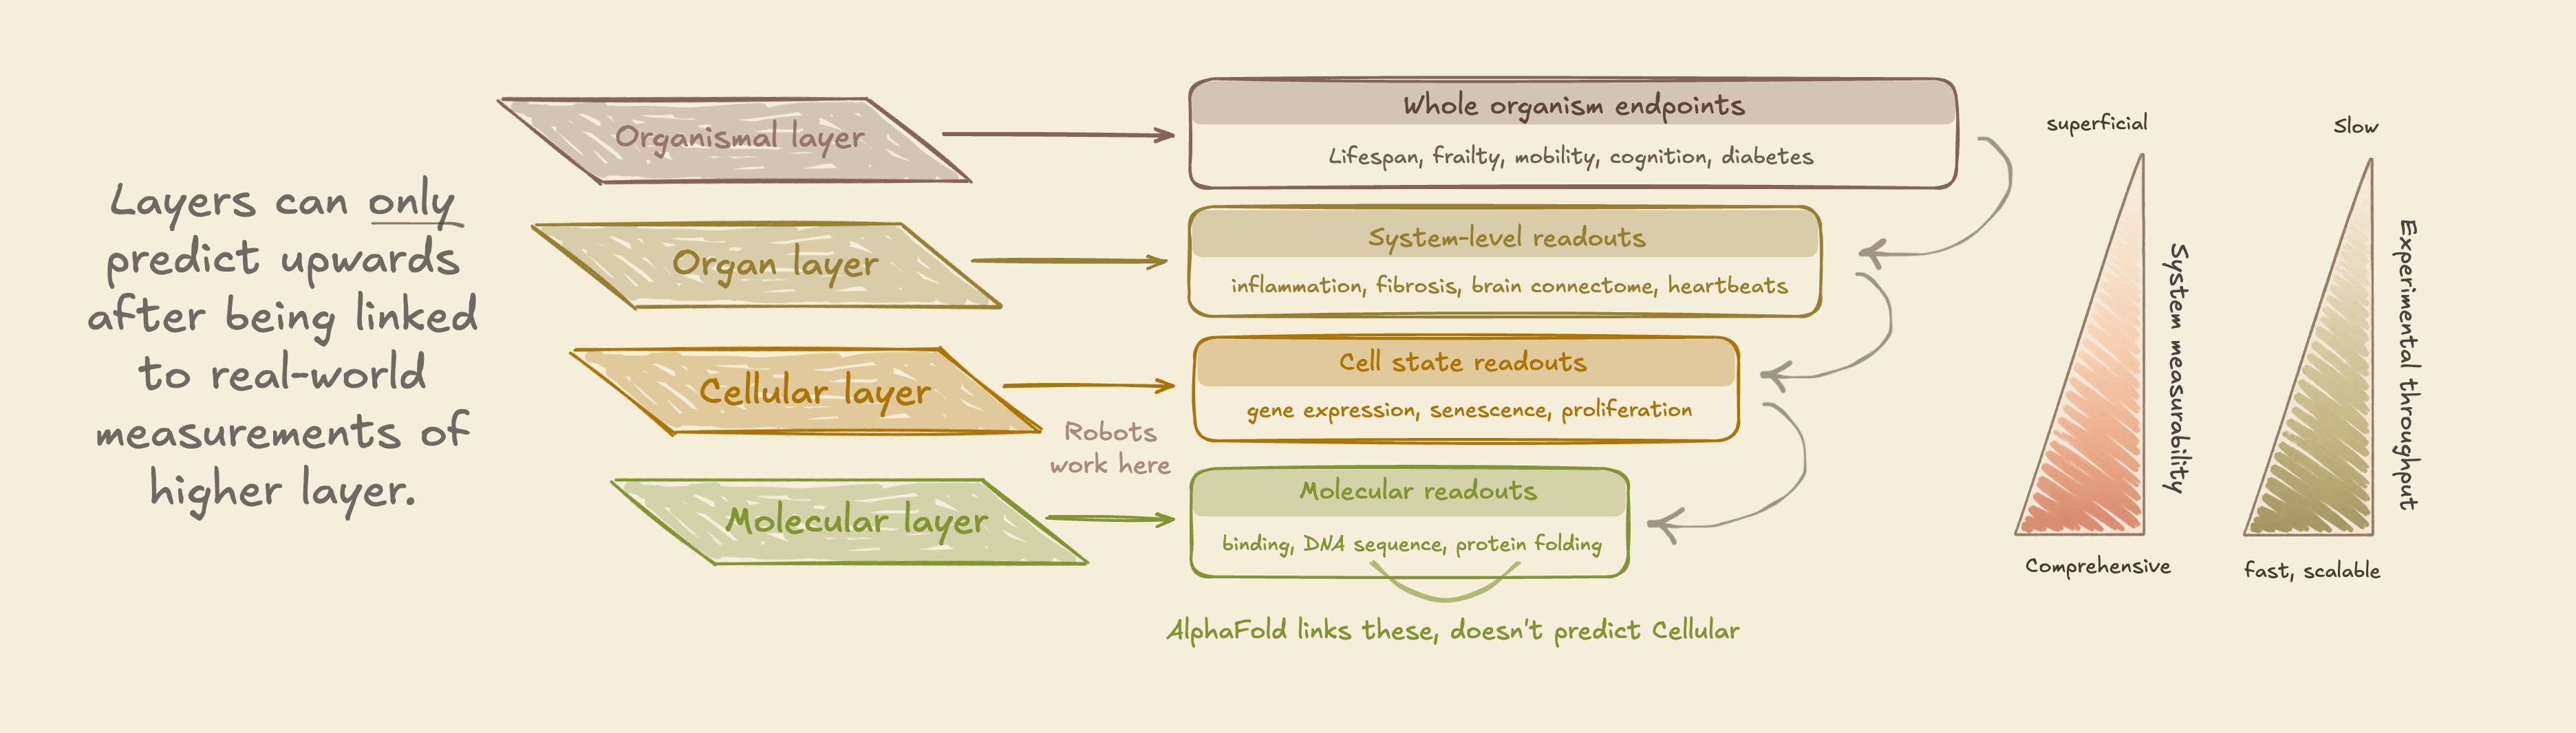
This is why predicting protein structures give us folding and some genetic diseases, but no cure for Alzheimer's or other complex diseases. Why the Human Genome Project alone didn’t lead to a plethora of cures. Why CRISPR hasn’t either, despite being a magnificent genomic tool. The problems longevity seeks to solve live at layers 3 and 4. Finding solutions requires hard-earned data from those layers.
Richer data is better, but isn’t sufficient unless it contains task-relevant answers.
But here biology runs into its own uncertainty principle: We can learn a little about a system while preserving its state, or we can cut its time short to learn more. Take heart failure. We can measure the output of the organ with an echocardiogram or a blood test. In animal models we can stop the system, take it apart, and take images of the tissue and measure molecules within its cells at that instant. Measuring the visual and molecular state of cells after a treatment improves function at layer 3 is a go-to experiment for linking layers 2 and 3, but it captures the new state without the path that got there. Cytokine cascades diffusing between cells, and countless other mechanisms, cannot be measured continuously without destroying the system.
The speed and cost of verification for that task determines how fast capability accrues.
The other challenge is time. Biology is the study of life, and life unfolds in time. Time can show us causal relationships, as in clinical trials. But layers 3 and 4 are time-costly. A drug for heart failure needs years of human follow-up to show whether it changes outcomes, and an aging intervention needs longer still because the endpoints are further away. Speeding this up with biomarkers requires us to run the slow study first to validate the biomarkers. UK Biobank is the most heavily mined longitudinal dataset in human biology, because it spans layers 1 (genetics and proteomics) and 4 (health outcomes). The interesting findings about disease and survival now coming out of it (like this paper) depend on the cohort having been tracked for fifteen-plus years. Even with an unlimited budget you could not generate UK Biobank by next month. Time-course is a non-substitutable input.
Relying on indefinite optimism would create another jagged frontier for AIxBio where cool advances flow to areas where we have or can quickly generate lots of task-shaped data (e.g. regulatory genomics, microbiology, or tracking health metrics and giving recommendations to stay within pre-defined ranges), or tasks that avoid unknowns (e.g. clinical trial documentation). Impact on longevity will remain on hold.
How we can enable AI to impact longevity
We now have principles for generating data that will enable AI to help longevity:
Maximize answers per unit time by starting the gating experiments now and avoiding sequential dependencies, since much biology can’t be sped up.
Data has to span the layer where we want AI to provide answers (physiological or organismal for longevity) to be task-shaped.
Richer data is better, since models can find structure we wouldn’t have known to look for.
When we want treatments, the data needs to contain or link to outcomes generated by interventions or by time, to enable causal inference.
Most obviously, we should start things that can’t be hurried. But even with the clock then ticking in our favor, core data generation tradeoffs remain. The good news is that the tradeoffs aren’t fixed. They can be molded by building the right bridges between layers, between systems, or between fast and slow sources of data.
Bridging layers
In humans and aging animals, intervention at scale isn't possible and longitudinal sampling is mostly restricted to scans and blood draws, while higher-layer pathology can't be modeled in isolated cells. But we can build biotechnological bridges between causal data and the layer we need answers from.
A simple example: You might collect blood from a few thousand autoimmune patients and run single-cell transcriptomics on their immune cells. You have a large cross-sectional dataset at the right layer, but attempting to predict disease outcomes purely from gene expression suffers from lack of verifiable outcomes. Adding a functional assay (like T-cell activation) prior to sequencing lets you couple gene expression to function, and function to patient outcomes.
A more ambitious example: pooled in vivo screening can bridge layers 2 and 3 by testing perturbations in cells inside living organs, such that physiological information is encoded in cell states. Many perturbations (causal) can be introduced into individual cells in the animal patient, with effects compared to controls in the same animal. This means that layer 3 information is encoded in perturbed cells, and can be interpreted with the help of independent paired datasets that link cellular signatures to organ-level physiological outcomes. Animal-to-human data paired datasets can further bridge preclinical experiments to human disease.
Bridging time
We can cheat time either by turning historical samples into task-shaped data, or by validating biomarkers to let faster systems stand in for slow ones2.
The US Veterans Affairs system has tracked millions of patients across decades of medical care and stored blood samples from many of them, but most of those samples have only been run through routine clinical chemistry. Adding proteomics, metabolomics, immune profiling, methylation, and cell-free DNA to a chosen subset would yield a longitudinal molecular dataset on a population whose health outcomes are already known, way faster (and cheaper) than starting a new cohort and waiting for outcomes. Stored samples from past clinical trials work the same way, with causal interventions baked in3. Thinking ahead, we can expect measurement technology to evolve (aided by AI), and so should prioritize banking additional samples from every longitudinal human study.
Experiments designed for future intelligence
The bridges described above can be part of any experiment we design today. But if we truly embrace intelligence abundance, we can combine them into experimental designs built to be maximally useful for AI:
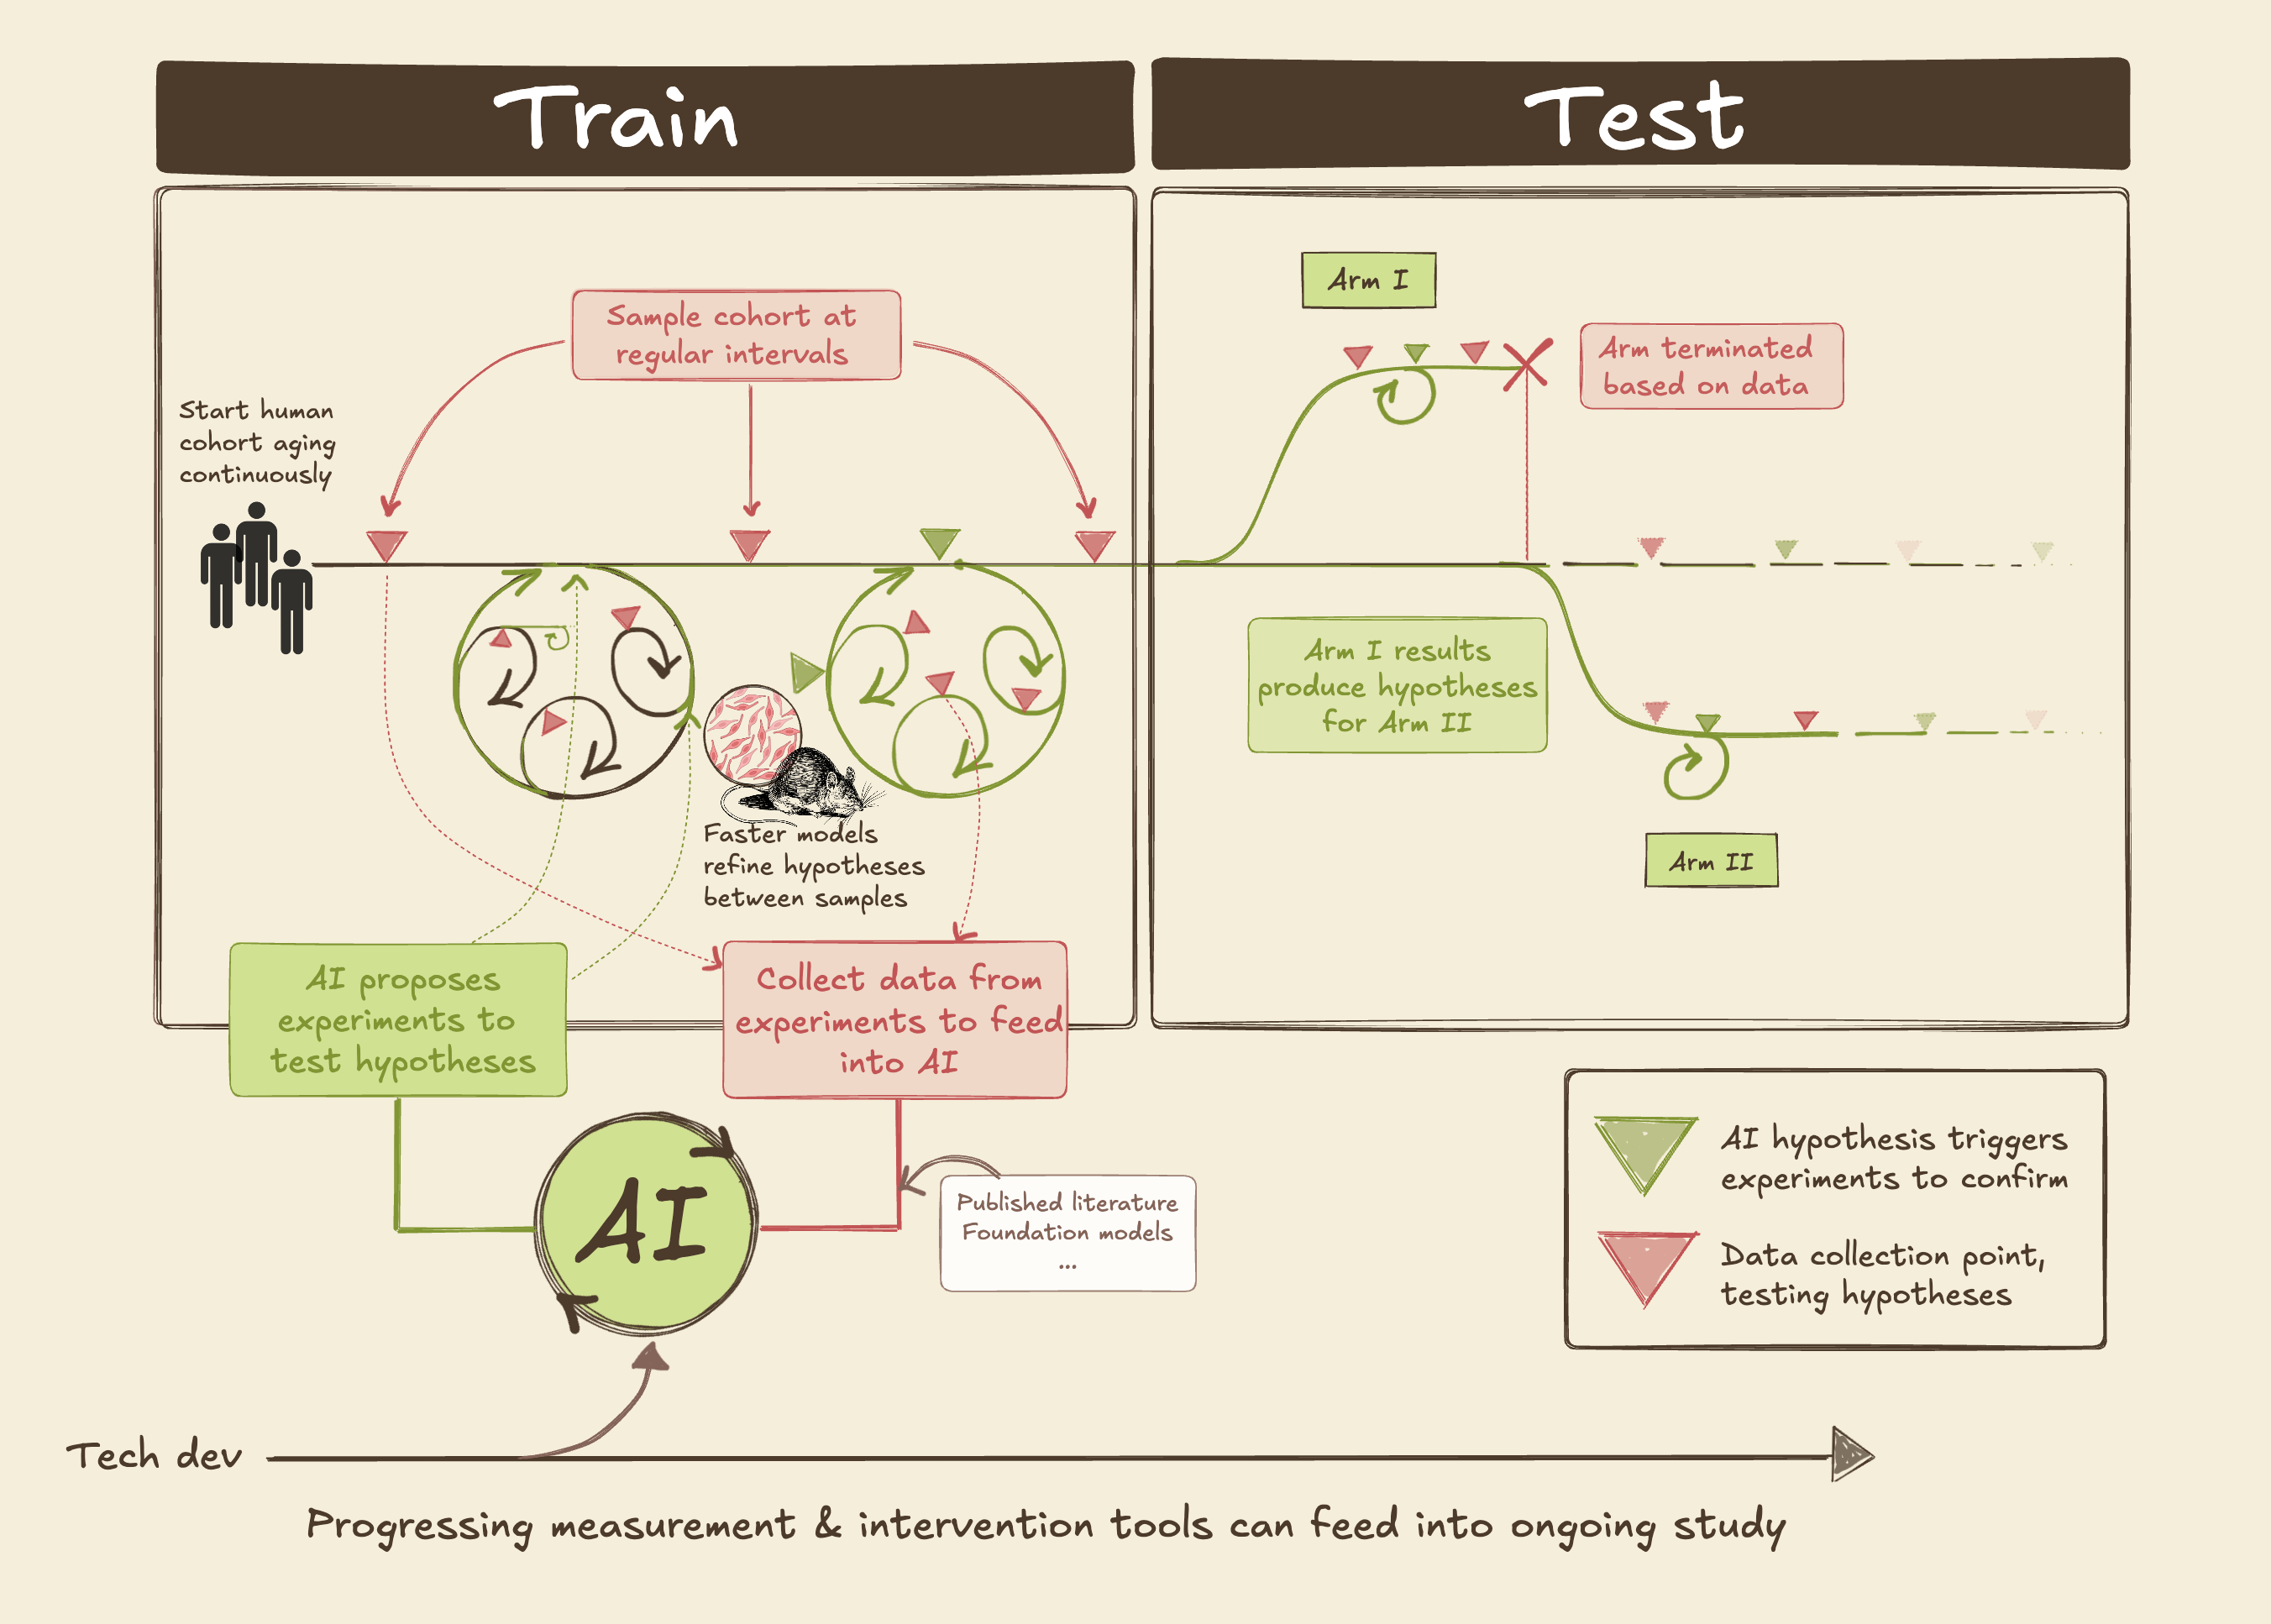
Start a middle-aged longitudinal human cohort now, large enough to capture aging trajectories across populations and split off groups later. Every three or six months, collect blood and run high-dimensional proteomics and other molecular assays. Periodically, layer on scans and functional measurements at the physiological layer: echocardiography, MRI, cognitive testing, frailty assessments. This fulfills ‘right layer’, ‘rich data’, and ‘longitudinal for causality’.
Multiple months between hypothesis testing is much slower than AI would like, so we add a fast experimental loop appropriate for specific hypotheses. The AI ingests each new sample alongside the prior timepoints, the published literature, and the participants’ clinical data, then proposes causal hypotheses about what’s driving the trajectories it sees. A hypothesis that a specific inflammatory signal sits upstream of kidney decline can be tested in mice perturbed to match patients, while finding causal drivers among broad molecular changes can be tested with in vivo pooled screens. Because these systems run faster than human aging, each new sampling timepoint arrives with refined hypotheses and tightened predictions for what each participant's sample should show, without needing to reset the aging clock.
When the prediction loop is calibrated well enough to be trusted, the cohort extends into an adaptive prevention trial4. The regulatory and ethical frame changes because you’re now intervening, but the experimental design carries over5 with one critical addition: because the AI already predicts each participant’s individual trajectory from the observational phase, we can compare effects both to the predicted progression of the individual patients, and to their peers in the control group. The AI commits to a specific prediction before each time point, and the measurement either confirms the intervention worked as predicted or shows where the model is still wrong. Compared to a conventional trial that waits years for arm-vs-arm divergence, here every datapoint is a verification event. This fulfills the criteria we laid out: We’re starting the slowest part (human aging) right away, but rather than waiting for one long trial we add multiple data feedback points, spanning physiological layer human data with faster loops of causal intervention data. Starting such a trial does not require new technology (but the trial design can adopt new tech as needed), it only needs foresight and commitment.
Objections to the layer limitation
Before we conclude, I want to address the common arguments for an imminent biological data abundance that would rewrite the rules we’re currently operating under.
The most common idea to save AI from physical reality is automated labs. This is a natural idea in part because it’s already happening: biopharma has been using liquid handling robots to test massive drug libraries for years. But whether done by pharma or AI-first biotechs, the automation never goes beyond the cell layer, because today's robots lack the manual dexterity for animal work. Even on Elon timelines, human-equivalent dexterity is a few years out and scaling robotics to ~double current R&D work will take a decade6. This can and should happen, but even that doubling of capacity will leave AI starved for physiological data.
If higher-layer behavior is in principle derivable from sufficient lower-layer measurements, scaling lower-layer data collection could yield higher-layer answers without measuring them directly. And layer 2 costs are coming down fast7. However, even our lower-layer measurements only sparsely capture biological reality. Single-cell sequencing captures roughly a third of the mRNAs in a cell, itself a fraction of total RNA. Then there are ~10¹⁰ proteins, along with their splice variants and post-translational modifications. And lipids, and things we don't yet know we should measure. All of this is captured at a single moment in time. We would need dramatically improved methods that fight physical reality to generate data to resolve even weak emergence.
If physical experiments are hard, could we just simulate them with virtual experiments?8 The critical question for longevity is whether we would be able to simulate physiological layers without data from those layers. We could discuss how compute-intensive simulations would be under different assumptions9, but the strongest evidence against this possibility is that none of the virtual cell models in development make use of AI breakthroughs from the molecular layer. AlphaFold and its successors have hugely improved protein structure modeling, and genomic models can simulate evolution and predict gene expression. But AlphaFold is not part of any frontier virtual cell model. One leading model, X-Cell, uses protein interaction data extensively, and notably relies on past experimental observations rather than AlphaFold predictions. Rather than build a model from subcomponents that do well at predicting molecular outcomes, every virtual cell model is based on cell-level measurements like imaging or RNA sequencing of whole cells. In other words, data at the layer the model is attempting to predict.
Conclusion
It’s possible that sheer scale of data centers and experiments on isolated cells in plastic wells will end up unlocking biological understanding that fundamentally changes how we approach curing disease. But many billions of dollars are already backing this hypothetical, across frontier AI labs, biotech MegaCos, and plentiful funding for AIxBio startups. The broader thrust of AI for bio is not focused on the problems particular to longevity, and the longitudinal cohorts and bridging datasets that would enable AI-driven longevity research mostly don’t exist yet. The time to start them is now, because the data takes years to mature regardless of how fast intelligence scales. If we want to maximize the probability of longevity benefitting from AI in time to yield medicines in our lifetimes, it seems wise to allocate at least 5-10% of AIxBio funding to the type of enabling work described here.
I’m grateful to Marton Meszaros, Effie Klimi, Hannu Rajaniemi, Julie Vaughn, Henry Miller, Alex Epstein, Michael Reisman, and Oliver Hahn for feedback on early versions of this essay.
To make the assumed acceleration explicit, this post assumes that by 2027 AI agents will be able to work through problems spanning roughly a week, with superhuman reasoning and the ability to ingest all published knowledge. This will generally be available at <<1% of the cost for humans to do the same. A double digit percentage of human work on computers will be automatable.
If we had biomarkers that reliably tracked aging, we could shorten longitudinal experiments from decades to months. Validating a biomarker requires linking early measurements to outcomes that arrive years later, across relevant conditions, which itself takes years. But we can bridge: by deliberately building biomarkers from molecular features that are conserved across species, like circulating proteins, and verifying that they behave the same way in mice and humans under matched perturbations, mouse studies can become a fast iteration loop for human-relevant questions. The NIH’s Interventions Testing Program has the right structure for this in mice (controlled lifespan studies with known aging-modulating interventions) and has provided multiple positive and negative controls, but doesn’t currently collect the molecular data needed. A Clock Assessment Program could run treated cohorts but with rich -omics at fixed timepoints, against which candidate clocks could be benchmarked.
Impetus has funded -omics on past clinical trials, which expanded into the FAST initiative.
The architecture proposed here borrows from several existing efforts. Adaptive platform trials such as I-SPY 2 (breast cancer) and REMAP-CAP (community-acquired pneumonia, repurposed during COVID) demonstrated that continuous, multi-arm trial designs with Bayesian updating can run more efficiently than the conventional fixed model. Continuous-monitoring longitudinal cohorts such as Verily’s Project Baseline pioneered deep multi-modal phenotyping at the individual level, and the All of Us Research Program is building a longitudinal human dataset at million-person scale. On the aging-specific side, the TAME trial proposed an aging-as-indication framework, and the ARPA-H PROSPR program plans to generate biomarker data alongside therapeutic testing. The Biomarkers of Aging Consortium has been working on the human-clock validation problem from the data-analysis side. What I am proposing is a synthesis that none of these individually represents: a longitudinal human cohort built from day one to feed an AI-driven hypothesis-and-experiment loop with deliberately matched fast-system experiments, with the cohort itself eventually becoming the trial. Each component exists in some form, but the integration is the point.
And we’re seeing experiments in this direction. The FDA recently announced a pilot program for real-time review of clinical trial data, with AstraZeneca and Amgen as the first oncology partners. The initiative gives FDA reviewers continuous access to safety and efficacy data as it accumulates, rather than requiring a single review at trial completion.
Speaking to robotics founders, the most common belief is that we’ll achieve ‘human equivalent’ capabilities across ~all experimental biology work between 2027 and 2029. Manufacturing will then need to scale, with optimistic public statements claiming we’ll produce a million sub-$100K robots per year by 2030. As a crude estimate, if we assume that the ~3M biomedical researchers worldwide work on physical experiments say 25 hours per week, ~500K human-equivalent robot systems with 90% uptime constitute a doubling of output (assuming that both human and robotic researchers use AI equally for intellectual work, and that this is no longer a bottleneck).
To estimate fractional deployment into biomedicine, we can work backwards from the total revenue consider that the current (i.e. what ultimately motivates R&D). Currently, US healthcare is ~5T/yr and projected to rise to 7T by early 2030s. ~10% of that is medicine, the rest services and admin. The greatest increase in the fraction of healthcare spending going to medicines was 7→11% in the 1990s. If we assume twice that increase, a doubling of drug spend as fraction of healthcare, we’d have US biopharma revenue from medicine of ~1.4T/yr. Assuming global revenue continues to be ~2x US, and that ~25% is from generics that don’t spur research, total R&D revenue pie is 2.1T/yr. Profit margins are ~30%, so spend to acquire that revenue is ~1.47T/yr, of which average R&D is ~20%, so 294B/yr. ~90% of that is clinical trials, and half of the research is personnel. So in the end, ~15B/yr that is worth replacing with robots, compared to estimates of robotics in manufacturing being somewhere between 200B and 300B. So overall, we might crudely expect 5% of robots being deployed to biomedicine.
Thus, if we are producing a million robots with capabilities matching a human scientist per year by 2030, and 5% are deployed to biomedicine, we might double research capacity somewhere in the second half of the 2030s.
We will cover this in more detail in a separate essay, but the cost to e.g. perturb and RNA sequence one billion single cells covering removal of every gene in the genome has gone from ~$100M in 2020 to ~$10-15M today, and is projected to be ~$1-2m by 2030. The cost curves for both DNA sequencing (“RNA sequencing” actually converts RNA to DNA before sequencing, so shared tech) and reagents specifically to label single cells before sequencing have been decreasing at a ~constant rate for more than a decade, so this projection seems reasonable. At today’s cost, only large consortia and well-funded private initiatives can undertake such an experiment. By 2030, dozens to hundreds of large academic labs will be able to afford such an experiment, which will increase the number of contexts where we have such cellular data by one or two orders of magnitude (though data from living systems would likely still be scarce).
Virtual cells are a major topic in biology today. The idea is that by scaling data generation (often single-cell -omics) and computational models, we’ll be able to predict how cells move between states (though please don’t ask for a formal definition of cell state). The most extensive whitepaper on virtual cells is from CZI, Stanford & Genentech. At least two compelling positions, from CZ Biohub and Sri Kosuri, present skepticism that larger scale experiments and LLMs are sufficient for a useful virtual cell. Multiple efforts are scaling fast, with Arc Institute among the most visible. If such efforts are successful, not having to wait for atoms to move around could conceivably increase research velocity many-fold. In practice as of 2026, state-of-the-art models have become occasionally useful to researchers as a sanity check before running experiments, and only in areas where massive datasets exist.
In a scenario where we acquire enough layer 2 data that available compute barely allows us to run a simulated cell simultaneously, when would we be able to scale to an organ? A human heart has ten billion cells. Even if modeling only a thousandth of a heart was enough to simulate the organ (and that ignores the pressure of blood being pumped, the lungs providing oxygen and gut providing nutrients, etc.), that’s twenty compute doublings (one or more decades) from when we first simulate a single cell. And this assumes linear scaling without emergent complexity as cells interact, which is not a good assumption. Interactions between non-identical components means superlinear scaling.
This was great bro! Good job!
I like this because it treats AI as a tool, not magic. If the biology is poorly measured, even a powerful model may only accelerate the parts we already understand. What kinds of longevity data do you think we most urgently need?